
Why Wages Have Stagnated While GDP Has Grown: The Proximate Factors

Real GDP per Capita & Median Weekly Earnings, 1980-2013

A.  Introduction

A healthy debate appears to be developing in the run up to the 2016 elections, with politicians of all parties raising the issue of stagnant wages.  Republicans have charged that this is a recent development, and the fault of Obama, but that is certainly not the case.  As the diagram above shows, real median wages have been stagnant since at least 1980, despite real GDP per capita which is 78% higher now than then.  Real median wages are only 5% higher (and in fact unchanged from 1979).  In a normally developing economy, one would expect real GDP per capita and real wages to move together, growing at similar rates and certainly not diverging.  But that has not been the case in the US since at least the early 1980s.

Why has such a large wedge opened up between worker earnings and GDP per capita?  This blog post will look at the immediate factors that lead from one curve to the other.  This will all be data and arithmetic, but will allow one to decompose the separation into several key underlying factors.  A future blog post will look at policies that would address those factors.

B.  Moving from Growth in GDP per Capita to Stagnant Real Wages

The progression from GDP per capita to real wages, with intermediate steps shown, looks as follows:

Going from GDP per Capita to Median Wage, 1947 to 2013:14

The chart here goes back further, to 1947, to show the divergence in recent decades in a longer term perspective.  The data come from the Bureau of Economic Analysis (BEA) or the Bureau of Labor Statistics (BLS).  As one sees, the curves moved together until around the mid-1970s, after which they began to diverge.

1)  Real GDP per Capita

Starting at the top, real GDP per capita (the curve in blue) measures the progression, in real terms, of GDP per person in the US.  GDP captures the value of all goods and services produced in the economy.  Its price index, the GDP deflator, is a price index for all those goods and services.  Although there have been temporary dips with periodic recessions, real GDP per capita has in fact grown at a remarkably stable long term rate of about 1.9% per annum going back all the way to 1870.  The growth rate was in fact a bit higher, at 2.0%, from 1947 to 2014, as the 1947 starting point was somewhat below the long term trend.  With this growth, real GDP per person was 3.75 times higher in 2014 than what it was in 1947.

2)  Real GDP per FTE Worker

But wages are paid to individual workers, and the share of workers in the population can change over time.  The share has in fact grown significantly over the post-war period, and in particular since about the mid-1960s, principally due to women entering the labor force.  There will also be demographic effects leading to changes in the shares of the very young and of retirees.

With a growing share of the population in the labor force, real GDP per full time equivalent (FTE) worker (the measure of the labor force used by the BEA) will grow by less than it will per person in the population.  The path of real GDP per FTE worker (the curve in green in the chart above), will rise more slowly than the path for real GDP per capita.  The curves start to diverge in the mid-1960s, when large numbers of women began to enter the labor force.

It should also be noted that the divergence in the two paths will not necessarily continue forever.  Indeed, the paths have in fact grown broadly in parallel from around 1997 until 2008 (when GDP per capita dipped in the downturn that began in the last year of the Bush administration).  The number of women entering the labor force reached a peak as a share of the labor force around 1997, and a decade later the first of the baby boomers started to retire.

Thus while such demographic factors and labor force participation decisions led to a significant divergence in the two paths (between GDP per capita and GDP per FTE worker) from the mid-1960s to the late-1990s, the impact since then has been broadly neutral, and might in fact go the other way going forward.

3)  Average Real Wages using the GDP Deflator

Next, workers are paid wages, not units of GDP.  Wages and salaries made up roughly half of GDP in 1947, with most of the rest accounted for by profits to capital.  And it stayed in the narrow range of 49 to 51% of GDP continuously until 1974.  The share then fell to 48%, where it held until 1981, and then began to deteriorate much more sharply, to just 42% as of 2013 (the most recent year with this data).

If the share of wages in GDP had remained constant, then the growth of wages per FTE worker would have exactly matched the growth of GDP per FTE worker.  But with a declining share of wages in GDP (with a growing share of profits as the mirror image), the curve (shown in brown in the chart above) of wages per FTE worker will rise by less than the curve of real GDP per FTE worker.

4)  Average Real Wages using the Consumer Price Index

The curves so far have been measured in real terms based on the GDP deflator.  The GDP deflator is a price index that takes into account all goods and services produced in the economy, and the weights in the price index will be in accordance with the shares of each of the goods or services in the overall economy.  But to an individual, what matters is the prices of goods and services that he or she buys.  This is measured by the consumer price index (cpi), where the weights used are in accordance with the expenditures shares of households on each of the items.  These weights can be significantly different than the weights of the items in GDP, as GDP includes more than simply what households consume.

The curve in orange in the chart above is then the average real wage but with the cpi rather than the GDP deflator used to account for inflation.  From 1978 onwards, the average real wage based on the cpi grew by significantly less than the average real wage measured in terms of the GDP deflator.  That is, inflation as measured by the items that make up the cpi grew at a faster rate, from 1978 onwards, than inflation as measured by the items (and their weights) that go into the GDP deflator.  Up until 1978, the cpi and the GDP deflator grew at remarkably similar rates, so the two curves (brown and orange in the chart) follow each other closely up to that year.

What happened after 1978?  The prices of several items whose weight in the cpi is greater than their weight in the GDP deflator began to rise more rapidly than other prices.  Especially important was the rise in medical costs in recent decades, but also important was the rise in housing costs as well as energy (with energy increases already from 1974).

Thus wages expressed in terms of what households buy (the cpi) rose by less, from 1978 onwards, than when expressed in terms of what the economy produces overall (the GDP deflator).

5)  Median Real Wages using the Consumer Price Index

The final step is to note that average wages can be misleading when the distribution of wages becomes more skewed.  If the wages of a few relatively well off wage earners (lawyers, say) rise sharply, the average wage can go up even though the median wage (the wage at which 50% of the workers are earning more and 50% are earning less) has been flat.  And that median wage is what is shown as the red curve in the chart.

[Technical Note:  The median wage series used here is the median weekly earnings of full time workers, adjusted for inflation using the cpi.  The series unfortunately only starts in 1979, but is the only series on the median, as opposed to average, wage I could find that the BLS publishes which goes back even as far as that.  The source comes from the Current Population Survey, which is the same survey of households used to estimate the nation’s unemployment rate, among other statistics.]

Since 1980 (and indeed since 1979, when the series starts), the median real wage has been flat.  This is not a new phenomenon, that only began recently.  But it is a problem nonetheless, and more so because it has persisted over decades.

C.  The Astounding Deterioration in the Distribution of Income Since 1980

Aside from demographic effects (including the impact of women entering the labor force), and the differential impact of certain price increases (medical costs, as well as others), the reason median real wages have been flat since around 1980 despite an increase of real GDP per capita of close to 80% over this period, is distributional.  The share of wages in GDP has been reduced while the share of profits has increased, and the distribution within wages has favored the better off compared to the less well off (leading to a rise in the average wage even though the median wage has been flat).

That is, the US has a distribution problem.  Wages have lost relative to profits (and profits largely accrue to the rich and wealthy), and the wages of lower paid workers have fallen even while the wages of higher paid workers have risen.

There are therefore two reasons for the distribution of income at the household level to have deteriorated since 1980.  And one sees this in the data:

Piketty - Saez 1945 to 2012, Feb 2015

This is an update of a chart presented in an earlier post, with data now available through 2012, and with the period from 1945 to 1980 included on the same chart as well.  The data came from the World Top Incomes Database (now part of the World Inequality Database), which is maintained by Thomas Piketty, Emmanuel Saez, and others.  The data is drawn from individual income tax return filings, and thus the distribution is formally by tax reporting unit (which will normally be households).  The incomes reported are total taxable incomes, whether from wages or from capital.

Over the 33 years from 1947 to 1980, average reported taxable incomes rose in real terms (using the cpi price index to adjust for inflation) by 87%.  The incomes of the bottom 90%, the top 10%, and the top 0.01%, rose by almost exactly the same amount, while the incomes of the top 1% and top 0.1% also rose substantially (by 57% and 63% respectively).  It is amazing how close together all these figures are.

This changed dramatically from 1980.  As the chart above shows, the curves then started to diverge sharply.  Furthermore, the average reported income rose only by 24% over 1980 to 2012, even though real GDP per capita rose by 73% over this period.  The 24% average increase can be compared to the 28% increase over the same years in the average real wage (based on the cpi).  While from two totally different sources of data (income tax returns vs. the national income accounts of the BEA) and measuring somewhat different concepts, these are surprisingly close.

But while average real incomes per household rose by 24%, the bottom 90% saw their real incomes fall by 6%.  Instead, the rich gained tremendously:  by 80% for the top 10%, by 178% for the top 1%, by 312% for the top 0.1%, and by an astounding 431% for the top 0.01%.

The US really does have a distribution problem, and this deterioration in distribution largely explains why real median wages have stagnated since 1980, while real GDP per capita grew at a similar rate to what it had before.

D.  Summary

To summarize, in the post-war period from 1947 to about the mid-1970s, measures of real income per person grew substantially and at similar rates.  Since then, real GDP per capita continued to grow at about the same pace as it had before, but others fell back.  The median real wage has been stagnant.

One can attribute this to four effects, each of which has been broadly similar in terms of the magnitude of the impact:

a)  Real GDP per worker has grown by less than real GDP per capita, as the share of those working the population (primarily women) has grown, with this becoming important from around the mid-1960s.  However, there has been no further impact from this since around 1997 (i.e. the curves then moved in parallel).  It may be close to neutral going forward, but was an important factor in explaining the divergence in the period from the mid-1960s to the late-1990s.

b)  The average real wage (in terms of the GDP deflator) has grown by less than real GDP per worker, as the share of GDP going to wages has gone down while the share going to profits (the mirror image) has gone up, especially since about 1982.

c)  The average real wage measured in terms of the cpi has grown by less than the average real wage measured in terms of the GDP deflator, because of the rising relative price since 1978 of items important in the household consumption basket, including in particular medical costs, but also housing and energy.

d)  The median real wage has grown by less than the average real wage (and indeed has not grown at all since the data series began in 1979), because of increasing dispersion in wage earnings between the relatively highly paid and the rest.

The implication of all this is that if one wants to attack the problem of stagnant wages, one needs to address the sharp deterioration in distribution that has been observed since 1980, and secondly address issues like medical costs.  Medical costs have in fact stabilized under Obama, as was discussed in a recent post on this blog.  But while several of the measures passed as part of the Affordable Care Act (aka ObamaCare) have served to hold down costs, it is too early to say that the previous relentless upward pressure of medical costs has ended.  More needs to be done.

Future blog posts will discuss what policy measures could be taken to address the problem of stagnant real wages and the deterioration in the distribution of income, as well as what can be done to address medical costs.
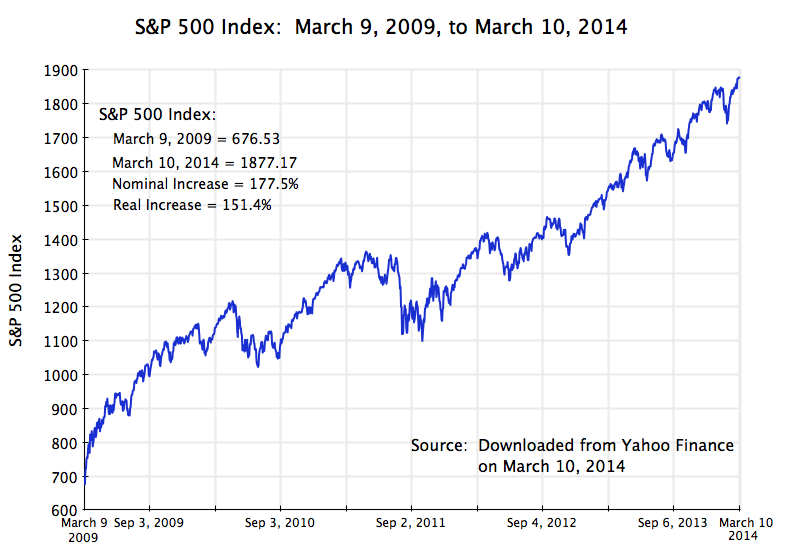
The Obama Bull Market Rally on Its Fifth Anniversary

S&P 500 Index, March 9, 2009, to March 10, 2014

Bull Markets, 1940-2014, updated to March 10, 2014

 
   Bull Market Rallies Since 1940
  Ranked by overall growth in real terms
Start Date End   Date Calendar Days Nominal % Change Real % Change Real Rate of Growth
Dec 4, 1987 Mar 24, 2000 4,494 582% 361% 13%
Jun 13, 1949 Aug 2, 1956 2,607 267% 222% 18%
Aug 12, 1982 Aug 25, 1987 1,839 229% 181% 23%
Mar 9, 2009 Mar 10, 2014 1,827 177% 151% 20%
Apr 28, 1942 May 29, 1946 1,492 158% 124% 22%
Oct 22, 1957 Dec 12, 1961 1,512 86% 76% 15%
Oct 9, 2002 Oct 9, 2007 1,826 101% 75% 12%
Jun 26, 1962 Feb 9, 1966 1,324 80% 69% 16%
May 26, 1970 Jan 11, 1973 961 74% 57% 19%
Oct 6, 1966 Nov 29, 1968 785 48% 37% 16%
Oct 3, 1974 Nov 28, 1980 2,248 126% 34% 5%

Today marks the fifth anniversary of the Obama bull market rally.  The rally began on March 9, 2009, just six weeks after Obama was inaugurated.  A reader of this blog suggested that on this anniversary, an update of previous posts on the strong performance of the stock market during Obama’s tenure (see here and here) might therefore be timely and of interest.

Stock market prices have indeed continued to rise, and as the table above shows, stocks during Obama’s term in office have now posted the fourth highest gains of any stock market rally since 1940.  Market rallies are defined as at least a 25% rise in the S&P 500 Index (in real terms), without a 20% fall.  Equity prices (as measured by the S&P 500) have risen by 177% in nominal terms since March 9, 2009, as of the close today.  The increase in real terms (using the CPI inflation index) has been 151%.  And since this rally is on-going, it could move further up in rank.  In addition, in just twelve more days (assuming the rally does not suddenly collapse) this rally will be the third longest in terms of calendar days of all market rallies since 1940.

It is also interesting to see how steady the upward progression has been, especially since September 2011.  This is shown in the graph at the top of this post.  I do not believe anyone had predicted this.

The rally could also end tomorrow.  All rallies eventually come to an end, and this one will as well.  But the rise in prices already achieved, the fourth largest since 1940, needs to be recognized.

Should Obama be given credit for this historic market rally?  Not fully.  I doubt that equity prices in themselves are a primary objective of what Obama has been trying to achieve.   Rather, the objective has been a stronger economy.  Regulatory as well as policy measures have been taken with the aim of strengthening the system, and this ultimately benefits business (as well as the population) as a whole.  This then helps equity prices.  Unfortunately, and as this blog has discussed in earlier posts, fiscal drag from cuts in government spending has held back the pace of the recovery, and this fiscal drag is continuing.  The economy could be doing better.  Nevertheless, there has been a partial recovery.  But it is not yet complete, nor as rapid as one would have had without the fiscal drag.

But what this strong growth in the stock market does clearly indicate is that the charges by Republican politicians that Obama has been bad for business (indeed a disaster for business many of them have said), has no basis.  If there were any truth to the charge, stock market prices would not be up by 177% in nominal terms (and by 151% in real terms) over the last five years, leading to the fourth biggest rally in stock prices in three-quarters of a century.

Vested Interests in Health Care: Spectacular Profits and Earnings for At Least Some Insurers and Providers

Cigna share price, Dec 1, 2003 to Dec 16, 2013.001

Ten-Year returns:  CIGNA = 361%;    S&P 500 Index = 70%

A.  Introduction

Earlier posts in this series on health care have documented how incredibly expensive the US health care system is (with costs almost $1 trillion more than would be the case if the US spent as a share of GDP what the second highest spending country does), and that the prices for the same procedure at different hospitals can vary by a factor of ten or even more.  Future posts will explore why this is the case.  But at this point it is worth reviewing how this US system of nominally competing private health insurance companies and health care providers nevertheless produces winners with truly astounding profits and personal compensation for those at the top.

The focus here will be on some of the numbers, documenting how at least some individuals and firms are doing very well in this non-transparent, non-competing, system.  The final section will add how this is taking place not because such insurers and health care providers are especially efficient at what they do, but rather because they are able to take advantage of a system of great inefficiency and waste.  And such winners now have a vested interest in keeping this badly functioning system in place.

B.  Spectacular Profits and Earnings of At Least Some Insurers and Providers

1)  To start, one can look at the stock market returns to investors in the major private health insurance companies.  The graph at the top of this post shows the ten year return (from December 2003 to December 2013) on an investment in the health insurer Cigna.  Such an investment would have received an overall ten year return of 361% (not counting dividends, which would have added to this).  That is, an investment of $10,000 in December 2003 would have grown to $46,100 by December 2013 (plus dividends).  Over this same period, the S&P 500 index (the generally used index of the overall stock market in the US, and shown as the orange line in the graph) would have grown by a pretty good 70%.  The Cigna return was more than five times as much.

2)  Other publicly traded health insurance companies have also done well.  Over this same ten year period, an investor would have received a return of 145% from an investment in Wellpoint, a return of 171% from an investment in UnitedHealth, a return of 318% in Aetna, and a return of 352% in Humana.  All of these are well in excess of the S&P 500 index return over this period.

3)  Wendell Potter, a former head of communications at two of the top health insurers (Humana and Cigna) who is now decidedly anti-insurance, presents in his 2010 book Deadly Spin figures on how much health insurance executives have been compensated.  Citing other sources that drew on corporate filings, he noted (page 139) that in 2007 the CEOs at the ten largest publicly traded health insurance companies received a combined total compensation of $118.6 million (an average of $11.9 million each).  From other corporate filings with the SEC, Potter noted (page 141) that between 2000 and 2008, the ten largest publicly-traded health insurers paid their CEOs a total of $690.7 million.  And in 2009, Wellpoint alone employed 39 executives who each collected total compensation exceeding $1 million.

4)  But annual compensation of even $10 million or more can substantially undercount what the CEOs of these health insurers ultimately receive.  According to a filing with the SEC, the Chairman and CEO of the health insurer Cigna retired at the end of 2009 with a retirement package worth $110.9 million.

5)  But the retirement package of the Cigna CEO was not the most generous among his peers.  The embattled CEO of UnitedHealth Care stepped down in late 2006 after being forced by the SEC to forfeit stock options worth $620 million.  The stock options in the company had been illegally backdated to make them especially profitable.  However the CEO was allowed to keep stock options worth $800 million, which was in addition to the $520 million he received in compensation from UnitedHealth while he ran the company from 1991 to 2006.  That is, this one individual received total compensation worth over $1.3 billion during his tenure as head of this private health insurer.

6)  Hospital providers have also done well.  Steven Brill, in his widely read article titled “Bitter Pill” published in Time Magazine in February 2013, calculated that in 2010 the prestigious MD Anderson Cancer Center in Houston, a non-profit that is formally part of the University of Texas system, had an operating profit of $531 million in fiscal year 2010.  This was equal to 26% of its revenue of $2.05 billion that year, which is a very generous margin for a service industry.

7)  Brill also noted the the total compensation of the president of the MD Anderson Cancer Center was $1.845 million that year (plus he earned more from other interests).  And he reported that six administrators at the Memorial Sloan-Kettering Cancer Center in New York earned over $1 million each at that one institution.

8) To coincide with the Steven Brill article, Time published figures on returns being earned by other major non-profit hospitals in the US.  The operating profits of the ten largest such hospitals (as measured by number of beds) varied from $118 million to $770 million (in the most recent year for which data is available).  The CEOs of these hospitals received between $2.1 million and $6.0 million in compensation from the hospitals (plus in general earned more from other interests as well):

Health - Profits & CEO Compensation at Non-Profit Hospitals, 2010.001

It should be added that not all hospitals are profitable.  The point, rather, is that at least some are highly profitable.

9) Using records that must be filed with the government each year, the California Nurses Association found that 100 executives at non-profit hospitals in California earned over $1 million each in 2010.  Four hospital groups accounted for 69 of these 100 high-earning executives, with the Sutter Health Network alone accounting for 28.  The top CEO compensation was $7.7 million in that year, and four CEOs earned $4 million or more.

C.  Yet Waste and Inefficiency is High

High profits and earnings could perhaps be justified if they were a consequence of highly efficient operators, providing an important service at low cost.  But that is not the case in the US:

1)  Overall Costs:  First, as has been noted before and discussed in the earlier blog post cited above, the US health care system is by far the most expensive in the world, with spending as a share of GDP which is 50% higher than in the second most costly country.  With almost $3 trillion being spent on health care in the US this year, that implies the US expenditures are about $1 trillion more than they would if it were spending (as a share of GDP) what the second highest country was spending.  And the US is spending $1.4 trillion more than it would if the US spent what the average OECD country does.

Yet as that blog post also noted, the results the US gets from such high spending are mediocre at best.  The infant mortality rate in the US is higher than in any other OECD country other than Mexico, Turkey, and Chile.  And life expectancy is only higher than in several OECD members with far lower income from Eastern Europe and Latin America.

If the US had an efficient health care system, it would not be spending so much for such poor results.

2)  Hospitals:  At least certain hospitals and their CEOs receive high incomes, as noted above, but there is no indication that this comes from being especially efficient.  Rather, the market in which they operate is highly fragmented, and as was documented in an earlier blog post, the variation in the prices they receive for similar medical procedures can vary by a factor of ten (or even more) between them.

As any economist will tell you, a normal market should not function that way.  In a normal market, one would not see much variation among prices (and what variation there is would be linked to some assessment of quality by the purchaser).  Economists call this the Law of One Price.  In such a market, profits will be earned by a provider who can provide the service at a lower cost (by being more efficient) and then selling it as this one price.  Furthermore, these more efficient producers, earning a higher profit than others who must also sell at this same price, will then expand to provide more of the product or service at this profitable price (profitable to them).  They will gain market share at the expense of the less efficient.  The price will drop, and over time the less efficient will be driven from the market, leaving the more efficient providers selling at what would then be a lower price than before.  In the end, only the most efficient providers will survive, and will earn a normal profit similar to that earned elsewhere and in other industries.

This process clearly does not happen in the market for health care provision.  Future blog posts will discuss why.  But briefly, the wide variation in prices makes it possible for even high cost medical providers to survive and even to thrive, and rewards those who are skillful at managing within this fragmented system.  It also rewards hospitals and other medical providers who enjoy market power vis-a-vis the insurer (by being one of only a few providers of this service within the region, for example by a hospital chain that might dominate the local market).  They will then be able to demand a high price, which the insurers (and ultimately the patient) will have little choice but to agree to.  Insurers, from their side, similarly seek to dominate any given local market.  Which side gains the upper hand depends on which is more successful in gaining market power against the other.

3)  Pharmaceuticals:  The pharmaceuticals industry also illustrates how an ability to exploit the rules in the system can lead to lead to big, indeed gargantuan, profits.  A good example was described in a recent Washington Post article, on the use of an expensive drug produced by Genentech for the treatment of age-related macular degeneration (AMD).  AMD is the most common cause of blindness among the elderly.  The Genentech drug, called Lucentis and developed through genetic engineering, is currently the most effective treatment for AMD.  Essentially the same drug, called Avastin for this purpose and also made by Genentech, is used for the treatment of certain cancers.  It can also be used to treat AMD, and many doctors notes it does this equally well as it is really the same drug.  But Lucentis costs $2,000 per dose, while Avastin, when used in the dosage required for AMD, only costs $50 to $60 per dose.

Why would any doctor then use Lucentis rather than Avastin for the treatment of AMD?  Because Genentech has only sought and obtained formal FDA approval for the use of Lucentis for AMD, while deliberately not applying to the FDA for the approval of Avastin for this purpose (it is, however, FDA approved for certain cancer treatments).  And in their compensation from Medicare for treating their elderly patients for AMD, the doctors will enjoy a much higher return from using Lucentis rather than Avastin since Medicare pays them a certain mark-up over cost.  This mark-up will be far higher in absolute terms for using Lucentis.  But by using Lucentis, the Washington Post calculates that Medicare has spent $5.7 billion more over the last five years than it would had Avastin been used.  Genentech has benefited enormously by its decision not to seek FDA approval of Avastin for treatment of AMD.

4)  Private Health Insurers:  Private health insurers, and their CEOs, have enjoyed often staggering returns, as noted above.  Such high returns could perhaps be seen as justified if these insurers provided their services efficiently and at low cost.  However, the costs incurred by private health insurers (and passed on to their clients) are high.

Figures on the net cost of private health insurers (i.e. administrative costs plus profits) are provided in the files on US health care costs issued each year by the Centers for Medicare and Medicaid Services (CMS).  The most recent data available go through 2011.  The “net costs” of private health insurers include all costs other than what the health insurers pay out to medical service providers on patient claims, and includes not only staff and office costs but also profits.  For brevity, this will sometimes be referred to simply as admin (or administrative) costs.

For 2011, the admin costs by private health insurers on private health insurance plans totaled $110.3 billion.  The benefits paid out under these plans came to $786.1 billion.  Thus the admin costs (including profits) amounted to 14.0% of the benefits paid.

The CMS data also provides such costs for Medicare.  The direct expenditures by government for administering this health insurance for the elderly totaled $8.2 billion in 2011, with benefits paid out of $521.6 billion, for a ratio of admin costs to benefits paid of 1.6%.  However, this would be a misleading figure as a substantial portion of Medicare is now administered by private health insurers under the Medicare Advantage program.  This program was expanded significantly in the 1990s and again with the passage of new legislation during the Bush administration, and in 2011 accounted for 25.3% of Medicare enrollees (see the table on page 168 of the May 2013 Medicare Trustees Annual Report).

The CMS data shows that private health insurers spent $24.5 billion in administering these Medicare Advantage programs.  One can then allocate Medicare payments to beneficiaries in proportion to the number of enrollees under either traditional government administered Medicare (74.7%) or under the privately administered Medicare Advantage (25.3%).  Assuming that the government’s $8.2 billion of admin costs was used solely for the programs it administered directly (even though a share would have been required to oversee the Medicare Advantage program), one can calculate the admin cost shares for the directly government administered side of Medicare, and for the Medicare Advantage program.

The result is that in 2011, the admin cost of the directly government managed portion of Medicare (for the 74.7%) came to 2.1% of benefits paid.  But for the privately administered side under Medicare Advantage (for the 25.3% enrolled there), the private admin costs alone came to 18.6% of benefits paid.  That is, private administration of Medicare programs was over nine times as expensive as direct government administration of such programs.

Future blog posts will discuss further why private administration of health care insurance is so expensive.  It is not simply profits, even though private health insurers have been substantially profitable.  It is also high costs from a business model that benefits from incurring costs to select a pool of insured clients who are relatively more healthy and hence are less likely to make insurance claims, and to deny claims when they can.

D.  Conclusion

Private health insurers and at least certain of the major health care providers have been hugely profitable in recent years, with the heads of these organizations often earning very large sums.  But such high profits and compensation have not been earned as a result of keeping down costs.  Costs in the US are especially high by international standards.  Rather, the high profits and compensation of those individuals at the top of their organizations have been made possible by a fragmented system, with little competitive pressure to bring down costs and prices.  The high returns go to those who are skillful at managing within such a system.

These high returns to at least some of the key players also creates powerful vested interests who benefit from a continuation of this high cost system.  Thus it should not be a surprise that powerful interests fear any major reform in the health care system, such as under Obamacare.  Even Obamacare, in the compromises it was forced to make in order to secure passage by Congress, was modest.  It focused on extending the availability of health insurance to those currently without insurance, with most of these to be enrolled in plans from the private health insurers.  There was no move to a single payer system such as from extending Medicare to the entire population, nor not even a public health insurance option which would be allowed to compete with the private health insurers.  There were only limited measures to try to contain health costs.  While it is still early, these limited measures appear to be having a positive effect on lowering costs, but they are not revolutionary.

More fundamental changes will be needed to bring down health care costs.  These will be explored in future blogs in this series on health care.

————————————

Update on January 9, 2014:  Following my posting of the blog above, Dr. Alex Horenstein of the Department of Economics at the University of Miami brought to my attention a paper he has prepared (with co-author Manuel Santos, also of the University of Miami) which addresses some of these same issues.  It comes to broadly similar conclusions on the high profitability of the health care and health insurance sectors, but is a much more rigorous piece than this blog post.  While portions of the Horenstein – Santos paper are fairly technical, and the piece is still a working paper that may be modified, there is a good deal of additional material on these issues in the paper and some readers may find it of interest.